ACSTRAUMAVAULTACUTE CARE SURGERY← ACS Vault
ACUTE ABDOMEN • SENIOR RESIDENT / SURGEON

Acute Appendicitis

A classic migrating-pain presentation that moves from bedside recognition to imaging interpretation and operative strategy.

PROTOTYPE REVIEW REQUIRED
01
The Call

20-year-old man with 18 hours of abdominal pain

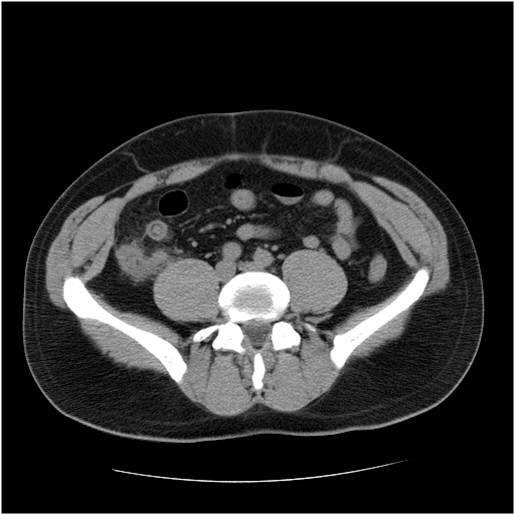
Pain began near the umbilicus and migrated to the right lower quadrant, with anorexia, nausea, low-grade fever, focal right lower quadrant tenderness and guarding.

T 38.0 C • HR 102 • BP 124/72
Migration of pain plus focal peritoneal irritation should make appendicitis a leading diagnosis while dangerous alternatives remain in the differential.
Read the Image • Clinical DataACS VISUAL
CT appearance of acute appendicitis from the ACS image archive.
Make the Decision • Commit to a Plan

A stable 67-year-old has 36 hours of RLQ pain, WBC 18,000, lactate 2.8, an appendicolith, marked inflammatory change and a 4-cm periappendiceal abscess. What is your best initial strategy?