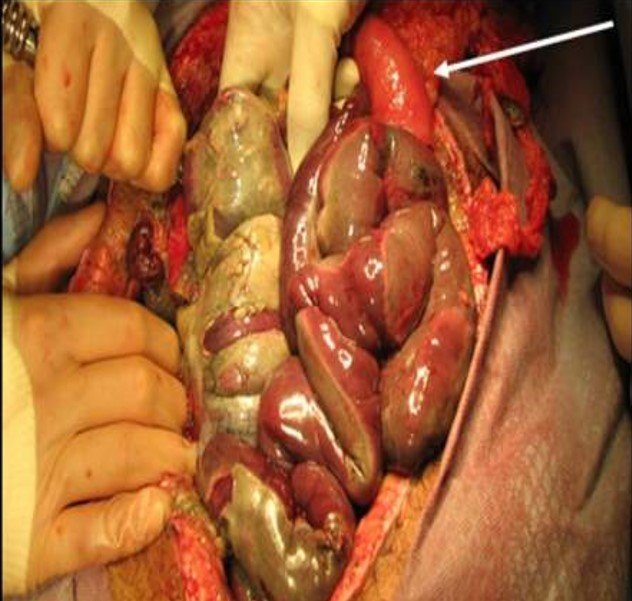
In the OR
Separate threatened bowel from irreversibly dead bowel.
- Inspect the entire bowel and identify the vascular/mechanical cause rather than judging one isolated segment
- Release strangulation or correct the occlusive process and reassess perfusion when restoration is possible
- Assess color, peristalsis, mesenteric pulsation and adjunct perfusion information in context; no single sign is perfect
- Resect clearly nonviable bowel while preserving potentially recoverable intestine when safe
- Use a planned second-look operation when viability remains uncertain or extensive ischemia risks unnecessary massive resection