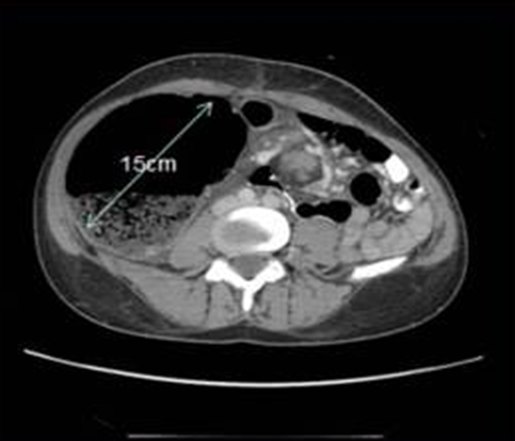
In the OR
Define viability before reconstruction.
- Identify the torsion or cecal bascule and the degree of right-colon mobility
- Assess the cecum, terminal ileum and proximal right colon for ischemia, gangrene or perforation
- Resection is favored because simple detorsion or fixation has meaningful recurrence risk
- Avoid aggressive manipulation of frankly gangrenous bowel before vascular control/resection when this may worsen contamination or physiologic insult
- Choose primary anastomosis versus diversion according to contamination, perfusion and the patient's physiology